PFOA and PFOS linked to higher rates of ER-negative breast cancer
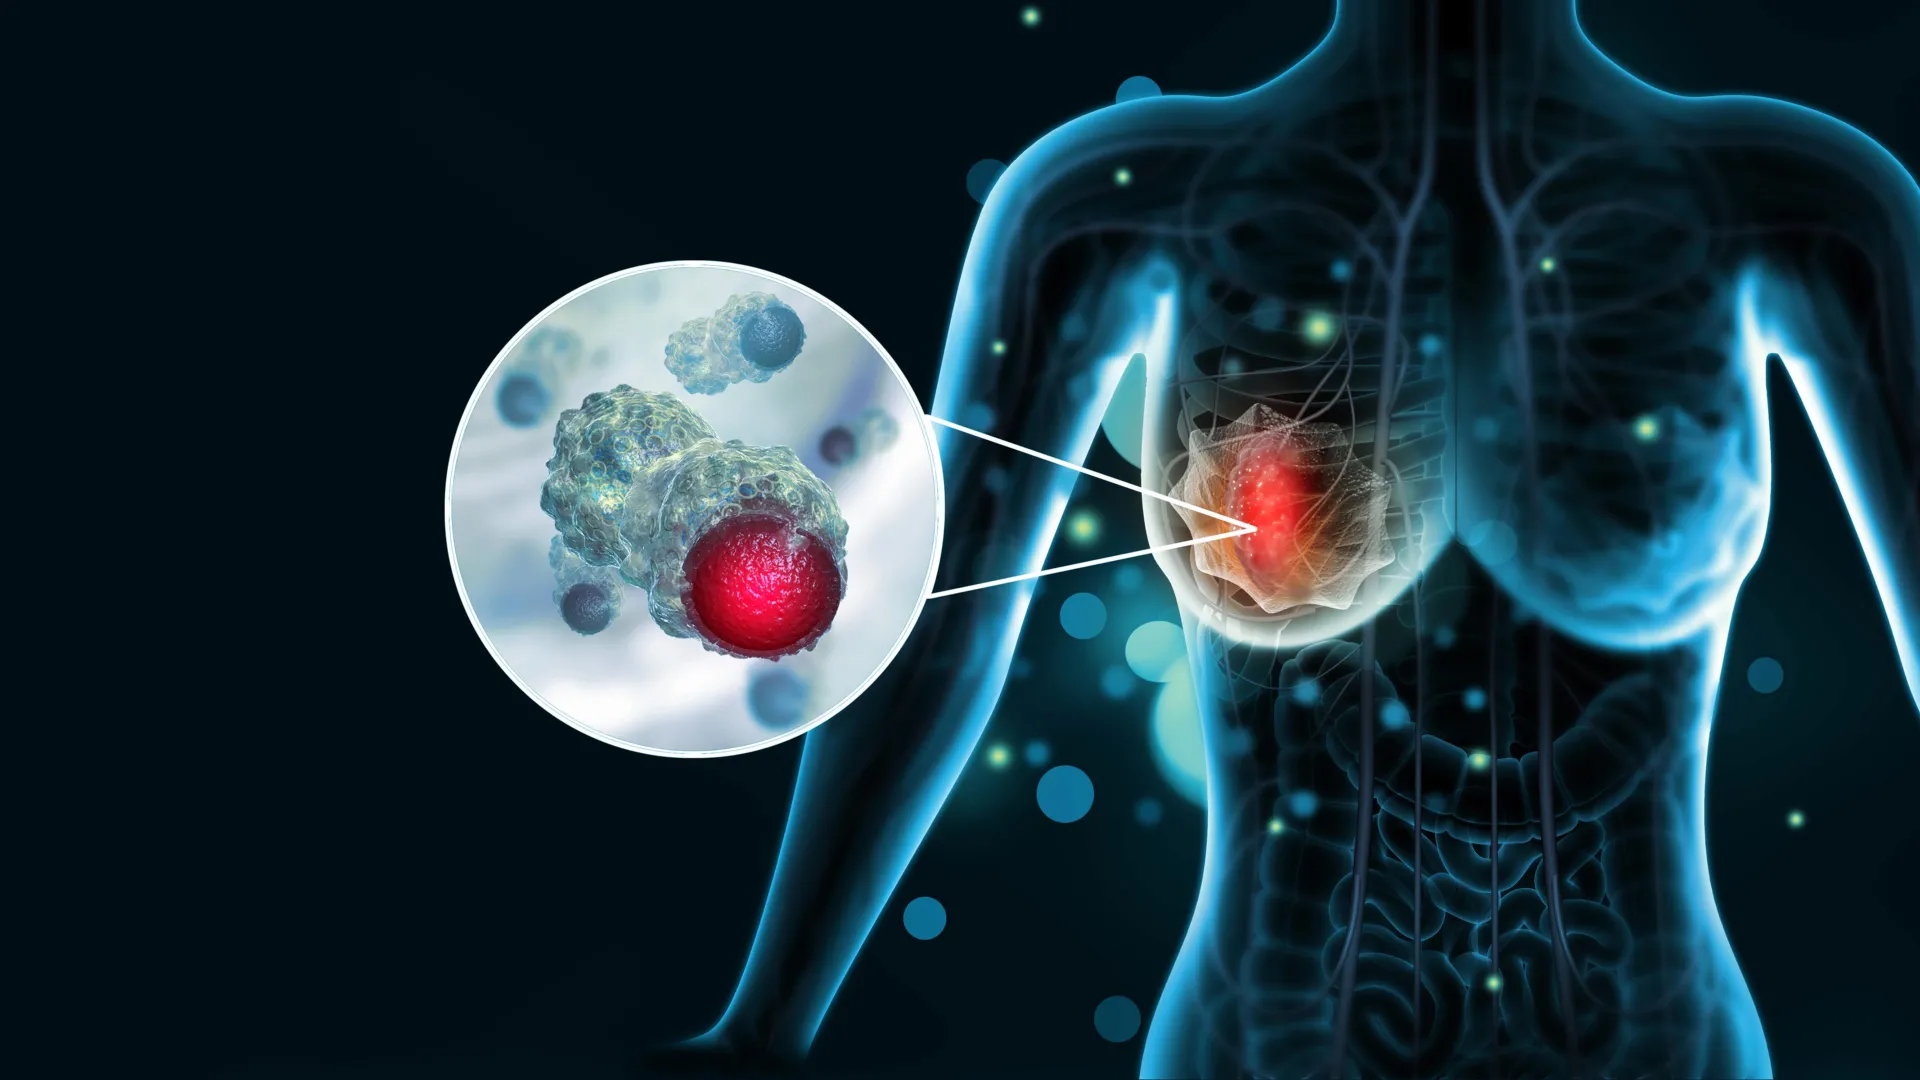
- Higher levels of PFOA and PFOS are associated with a higher incidence of ER-negative breast cancer
- The difference between the high- and low-exposure groups was 67% for PFOA and 93% for PFOS
- The study did not establish causation and found no clear link between these substances and breast cancer overall
What the NIH study found
Researchers at the U.S. National Institutes of Health reported a link between two common, persistent chemicals and ER-negative breast cancer. They are perfluorooctanoic acid, or PFOA, and perfluorooctanesulfonic acid, or PFOS. Women with higher concentrations of these substances in their blood were more likely to be diagnosed with this specific form of the disease. The finding points to a possible risk factor, but does not in itself prove that exposure to the chemicals directly causes cancer.
The key qualification is that the study found a link not with breast cancer in general, but with tumors that lack estrogen receptors. The researchers found no clear link between either PFOA or PFOS and the overall risk of breast cancer. Therefore, the finding cannot be applied to all forms of the disease or interpreted as proof of a generally increased risk for every woman with detectable PFAS. The study focuses on a specific tumor subtype and reports a statistical association that requires further investigation.
A comparison of groups showed that women with the highest PFOA levels had a 67% higher rate of ER-negative cancer than women with the lowest levels. For PFOS, the difference was 93%—almost double. These figures describe a relative difference between groups, not an individual’s absolute likelihood of developing the disease. The publication does not provide a basis for turning them into a personal forecast, so it would be incorrect to interpret the percentages as a chance of getting cancer.
How chemical exposure was assessed
Both substances belong to a large group of per- and polyfluoroalkyl substances known as PFAS. They are called “forever chemicals” because they break down slowly in the environment; they can also build up in the body and remain there for years. PFOA and PFOS were used in many everyday consumer products. Although these two compounds have largely been phased out and replaced with other PFAS, measurable amounts are still found in most people’s bodies.
To compare exposure with a subsequent diagnosis, the team studied blood samples collected years before the participants were diagnosed with cancer. They measured concentrations of 17 different PFAS in the samples. Collecting the samples in this order makes it possible to compare earlier substance levels with outcomes that occurred later, rather than relying only on measurements taken after diagnosis. However, the study still identifies an association in observational data: the design described does not turn it into proof that PFOA or PFOS causes cancer.
The analysis drew on the Sister Study, a project of the National Institute of Environmental Health Sciences, part of the NIH. From 2003 to 2009, 50,884 women aged 35 to 74 from the United States and Puerto Rico enrolled in the study. At enrollment, the participants had not had breast cancer, but each had a full or half sister who had previously been diagnosed with the disease. This is an important feature of the sample: it was drawn from women with a family history of the disease.
Why the ER-negative form warrants attention
For a separate analysis of PFAS, researchers used data from 1,609 women who later developed breast cancer and a comparison group of 2,269 women. This means the reported differences did not come from observing all 50,884 participants as one homogeneous group, but from a specific analytical sample within the Sister Study. Describing this sample helps convey the scope of the work, but does not justify treating its findings as an automatic measure of risk for every woman or for all population groups.
ER-negative tumors differ in that their cells lack the receptors through which estrogen can stimulate cancer growth. According to the article, these tumors often behave more aggressively and are generally associated with less favorable outcomes than tumors that respond to estrogen. At the same time, researchers know relatively little about the factors that increase the likelihood of ER-negative disease specifically. A possible link with persistent chemicals is therefore scientifically interesting, but for now it remains part of an ongoing investigation, not an established explanation for the origins of this form of cancer.
The authors note that they compared the results with earlier studies through a meta-analysis. Study lead Alexandra White said the pooled data point to an association between some older PFAS, including PFOA and PFOS, and an increased risk of ER-negative cancer—a subtype with few known risk factors. The study was published in the Journal of Clinical Oncology. Confirmation through analysis of previous studies strengthens the case for further research into monitoring, but does not overcome the limitations or prove a biological mechanism.
Limitations and questions for future research
The researchers suggest that PFAS exposure may be linked to processes unrelated to hormone signaling, pointing to what they describe as a stronger association with tumors lacking estrogen receptors. Possible explanations include changes in gene activity or immune system function. However, the authors did not directly examine these mechanisms. None of these explanations can therefore be considered a confirmed cause of the observed association; they are hypotheses for future research, not findings of the current analysis.
For now, the practical takeaway is limited to the fact that PFAS exposure may be modifiable: the authors note that people can take steps to reduce it. However, the study does not identify specific measures guaranteed to lower the risk of breast cancer, nor does it allow the effects of such actions to be calculated. Its findings may eventually help researchers explore ways to prevent aggressive tumors, but the association must first be confirmed and the underlying process understood. For now, this is an area for further study, not a ready-made recommendation.
The following questions remain open. The authors consider it important to study groups with higher PFAS exposure and communities where ER-negative cancer is more common, to clarify the strength of the observed association and understand whether the risk differs across populations. Another priority is to determine whether similar concerns apply to the new substances that replaced PFOA and PFOS. Because older compounds persist in the body, their gradual phaseout does not mean that exposure has already disappeared; however, its significance for risk remains to be established.
Source: ScienceDaily